

Unlimited certifications + CE, from $14/moAll certs + CE from $14/mo


Pediatric Bradycardia - Pulse & Poor Perfusion
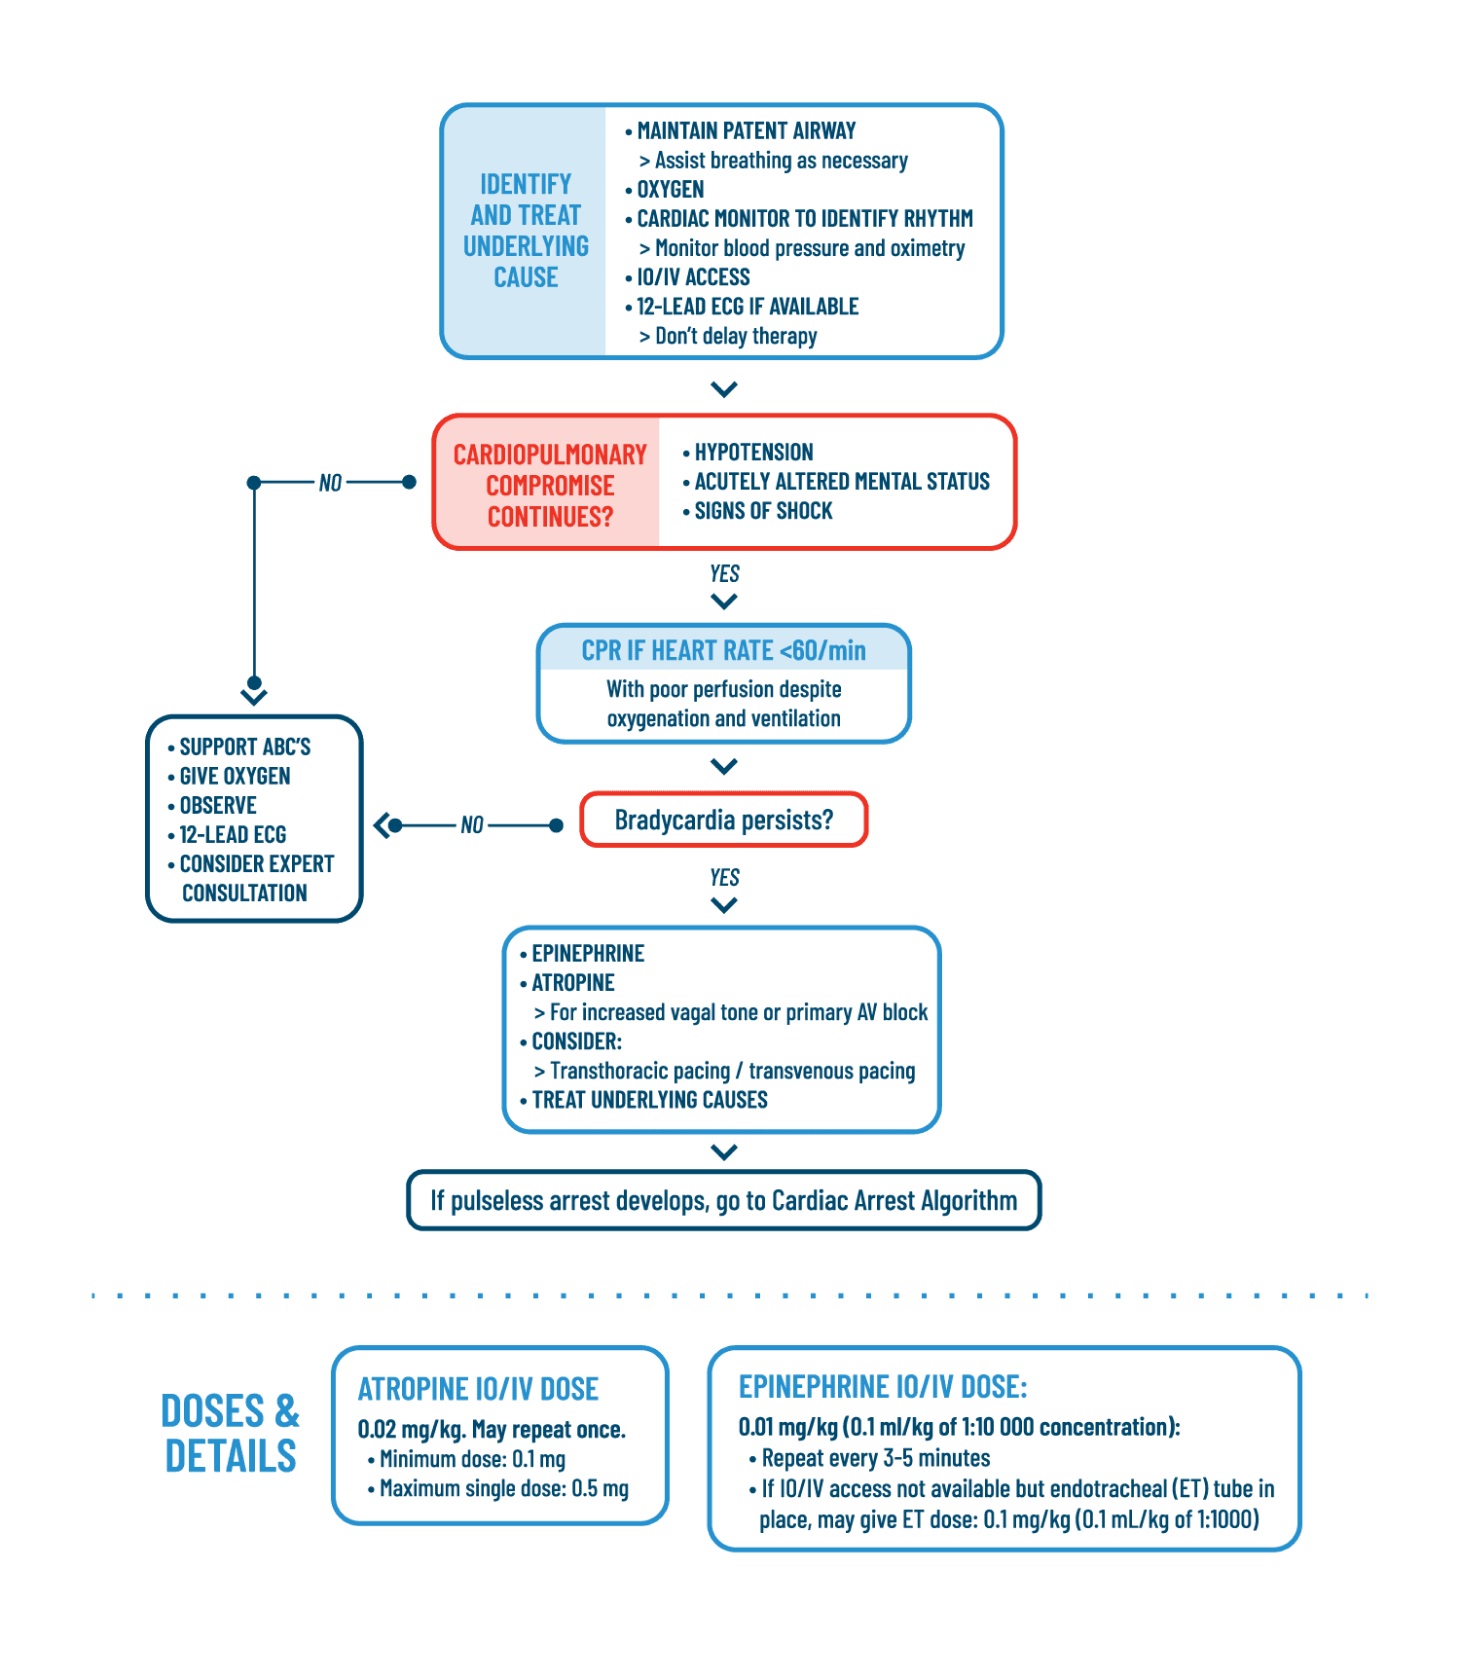
- CPR if HR below 60/min with poor perfusion
- Epinephrine 0.01 mg/kg every 3–5 min
- Atropine 0.02 mg/kg (max 0.5 mg)
- Consider pacing
In children, a slow heart rate with poor perfusion is usually caused by low oxygen and often comes right before cardiac arrest. Supporting breathing comes first, and CPR starts early if the rate stays below 60.
When to use it
An infant or child has a pulse, a slow heart rate, and signs of poor perfusion.
Step by step
Assess and support
Look for and treat the cause. Keep the airway open and assist breathing with oxygen. Attach a monitor, check blood pressure and oxygen levels, start IV/IO access, and get a 12-lead ECG if it does not delay care.
Is there cardiopulmonary compromise?
Look for low blood pressure, sudden confusion, or signs of shock.
No compromise
- Support ABCs and give oxygen.
- Observe closely and consider expert consultation.
Compromise present
- If HR stays below 60/min despite oxygenation and ventilation, start CPR.
If bradycardia continues
Give epinephrine. Give atropine for increased vagal tone or primary AV block. Consider transcutaneous or transvenous pacing.
If the pulse is lost
Go straight to the Pediatric Cardiac Arrest Algorithm.
Key drugs & doses
| Drug | Dose | When |
|---|---|---|
| Epinephrine | 0.01 mg/kg IV/IO (0.1 mL/kg of 0.1 mg/mL) | Every 3–5 min if bradycardia persists |
| Atropine | 0.02 mg/kg IV/IO (max single dose 0.5 mg) | Vagal tone or primary AV block; may repeat once |
Remember
- Good oxygenation and ventilation fix most pediatric bradycardia.
- Do not wait for drugs to start CPR when the rate is below 60 with poor perfusion.

Test your PALS
Knowledge
Our PALS practice exam includes questions on the pediatric algorithms, modeled on a real PALS exam.
Simple, affordable pricing
Select your Online ACLS, PALS, BLS, CPR or Neonatal Medical Certification Course below

The Advanced Cardiac Life Support (ACLS) is an accredited online medical certification course that teaches medical professionals to respond to nearly all cardiopulmonary emergencies.
Learn more
The Pediatric Advanced Life Support (PALS) Recertification instructs medical professionals on performing pediatric cardiopulmonary resuscitation in emergencies.
Learn more
The Basic Life Support (BLS) Recertification is intended to teach healthcare professionals the basic steps of CPR and rescue breathing for adults, children, and infants.
Learn more
Our online medical certification course for CPR, Automated External Defibrillator (AED), and First Aid is designed to teach adult, child, and infant CPR and AED use.
Learn more
The Neonatal Resuscitation Certification trains medical professionals in performing resuscitation procedures and life-saving techniques for newborns at the time of delivery.
Learn more