

Unlimited certifications + CE, from $14/moAll certs + CE from $14/mo


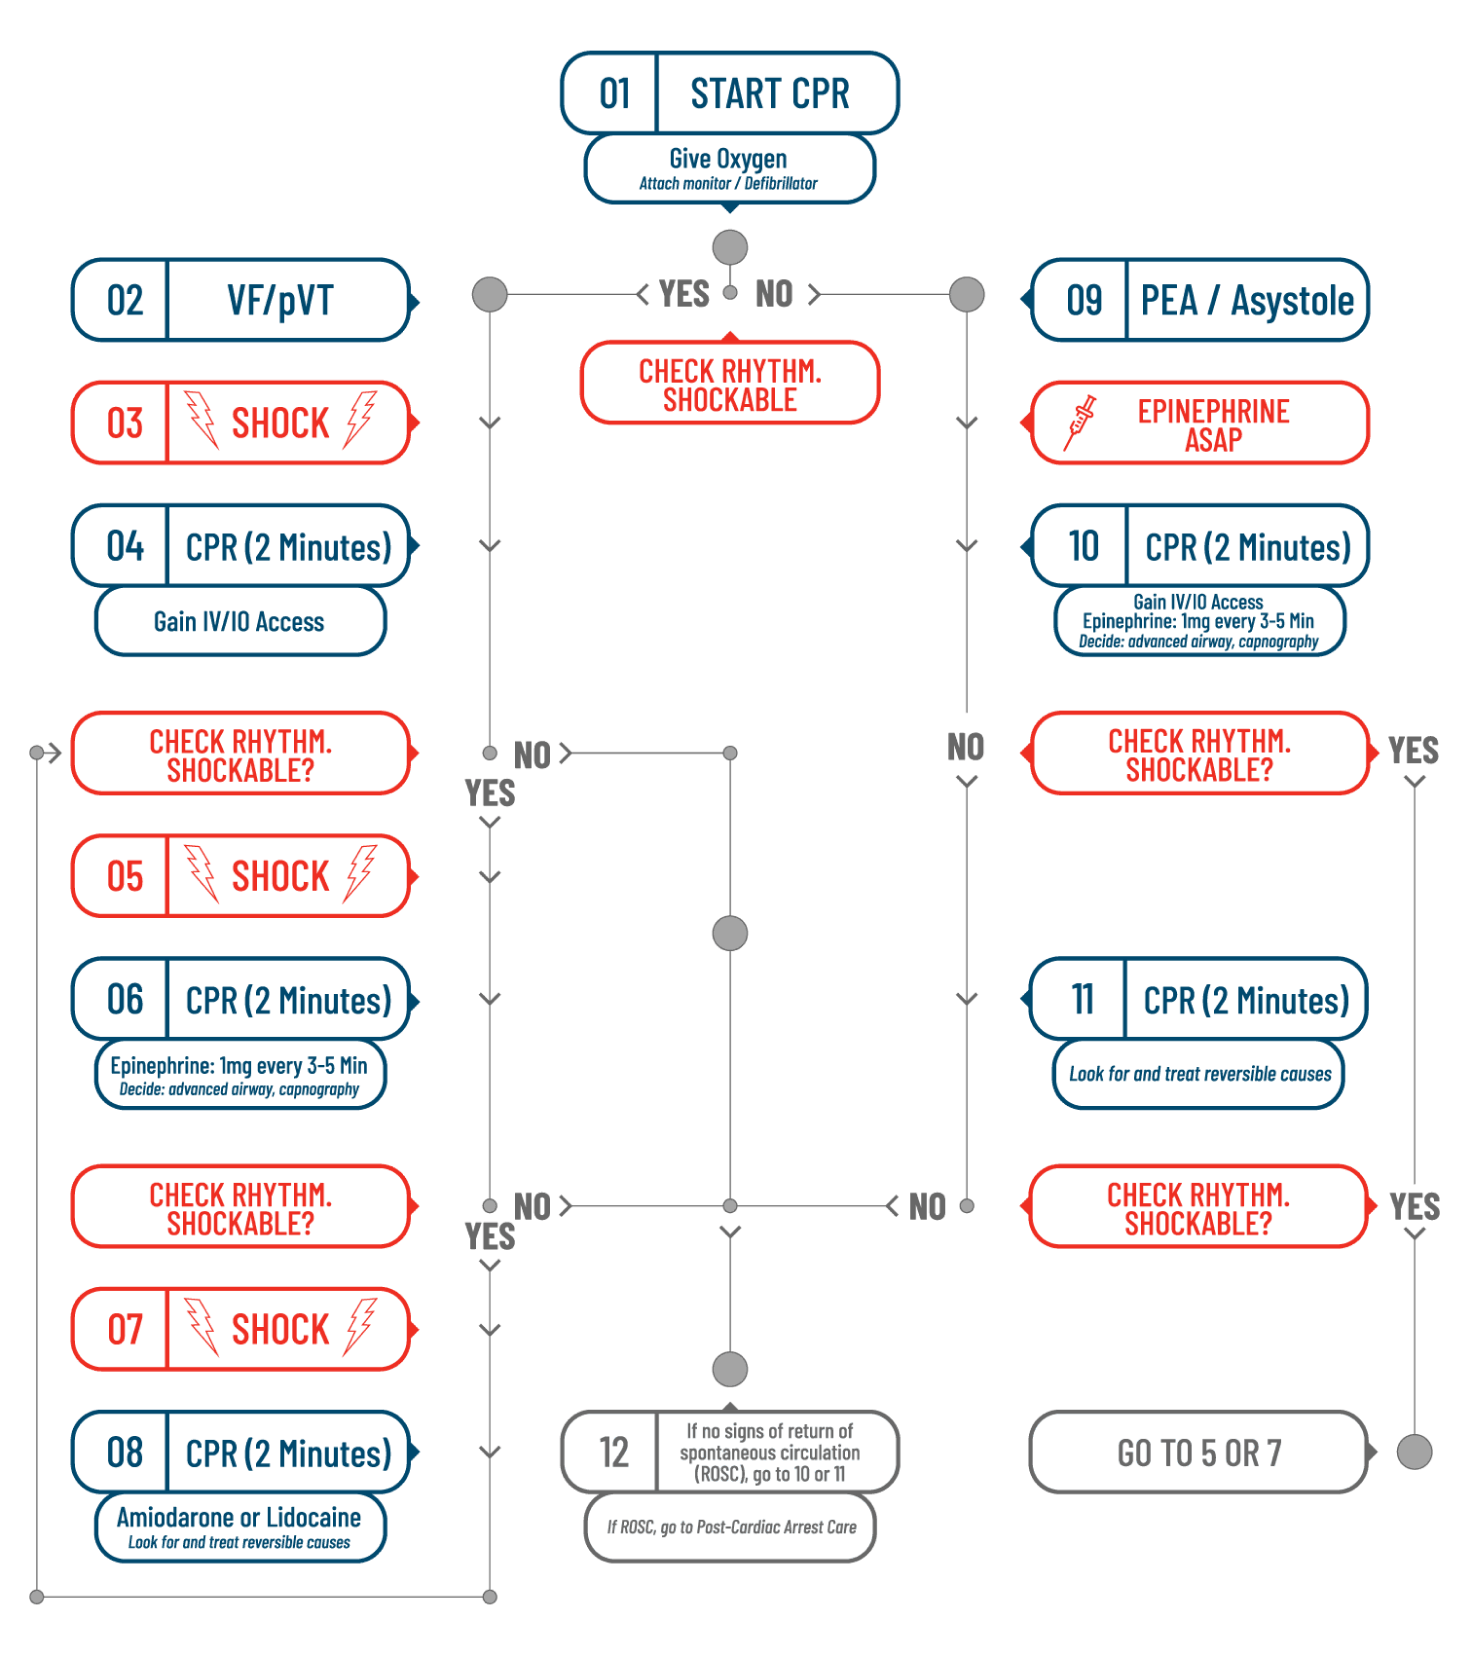
Adult Cardiac Arrest Algorithm
- 100–120 compressions/min
- Depth 2–2.4 in (5–6 cm)
- Rhythm check every 2 min
- Epinephrine 1 mg every 3–5 min
This is the most important algorithm in ACLS. When an adult has no pulse, your first decision is whether the rhythm is shockable (ventricular fibrillation or pulseless ventricular tachycardia) or non-shockable (pulseless electrical activity or asystole). That one decision sets the path for everything that follows.
When to use it
An adult is unresponsive, is not breathing or is only gasping, and has no pulse you can feel within 10 seconds.
Step by step
Start CPR
Begin high-quality chest compressions immediately. Give oxygen and attach a monitor/defibrillator as soon as it arrives.
Check the rhythm
Pause compressions for less than 10 seconds to read the monitor.
Shockable: VF / pVT
- Deliver 1 shock, then resume CPR immediately for 2 minutes.
- Get IV/IO access during this cycle.
- After the 2nd shock: epinephrine 1 mg every 3–5 minutes.
- After the 3rd shock: amiodarone or lidocaine.
Non-shockable: PEA / asystole
- Do not shock. Continue CPR for 2 minutes.
- Give epinephrine 1 mg as soon as possible, then every 3–5 minutes.
- Search hard for a reversible cause; it is often the only fix.
Keep cycling every 2 minutes
Check the rhythm, shock if it is shockable, and resume CPR right away. Switch compressors at every rhythm check to avoid fatigue.
Consider an advanced airway
Use waveform capnography to confirm tube placement and track CPR quality. Once the airway is in, give 1 breath every 6 seconds with continuous compressions.
Treat reversible causes
Work through the H’s and T’s with your team: Hypovolemia, Hypoxia, Hydrogen ion (acidosis), Hypo-/Hyperkalemia, Hypothermia, Tension pneumothorax, Tamponade (cardiac), Toxins, Thrombosis (pulmonary or coronary).
Check for ROSC
Signs include a pulse and blood pressure, or a sudden sustained rise in ETCO2 (typically 40 mm Hg or higher). If present, move to post-cardiac arrest care. If not, keep cycling.
Key drugs & doses
| Drug | Dose | When |
|---|---|---|
| Epinephrine | 1 mg IV/IO | Every 3–5 min. Non-shockable: as soon as possible. Shockable: after the 2nd shock. |
| Amiodarone | 300 mg IV/IO, then 150 mg | For VF/pVT that persists after shocks. |
| Lidocaine | 1–1.5 mg/kg, then 0.5–0.75 mg/kg | Alternative to amiodarone. |
| Shock energy | Biphasic: 120–200 J (per device). Monophasic: 360 J | Every shockable rhythm check. |
Remember
- Push hard and fast and let the chest fully recoil.
- Keep pauses in compressions under 10 seconds.
- ETCO2 below 10 mm Hg means compressions need to improve.
- Never shock PEA or asystole.

Test your ACLS
Knowledge
Our ACLS practice exam includes questions pulled directly from a real ACLS exam.
Simple, affordable pricing
Select your Online ACLS, PALS, BLS, CPR or Neonatal Medical Certification Course below

The Advanced Cardiac Life Support (ACLS) is an accredited online medical certification course that teaches medical professionals to respond to nearly all cardiopulmonary emergencies.
Learn more
The Pediatric Advanced Life Support (PALS) Recertification instructs medical professionals on performing pediatric cardiopulmonary resuscitation in emergencies.
Learn more
The Basic Life Support (BLS) Recertification is intended to teach healthcare professionals the basic steps of CPR and rescue breathing for adults, children, and infants.
Learn more
Our online medical certification course for CPR, Automated External Defibrillator (AED), and First Aid is designed to teach adult, child, and infant CPR and AED use.
Learn more
The Neonatal Resuscitation Certification trains medical professionals in performing resuscitation procedures and life-saving techniques for newborns at the time of delivery.
Learn more